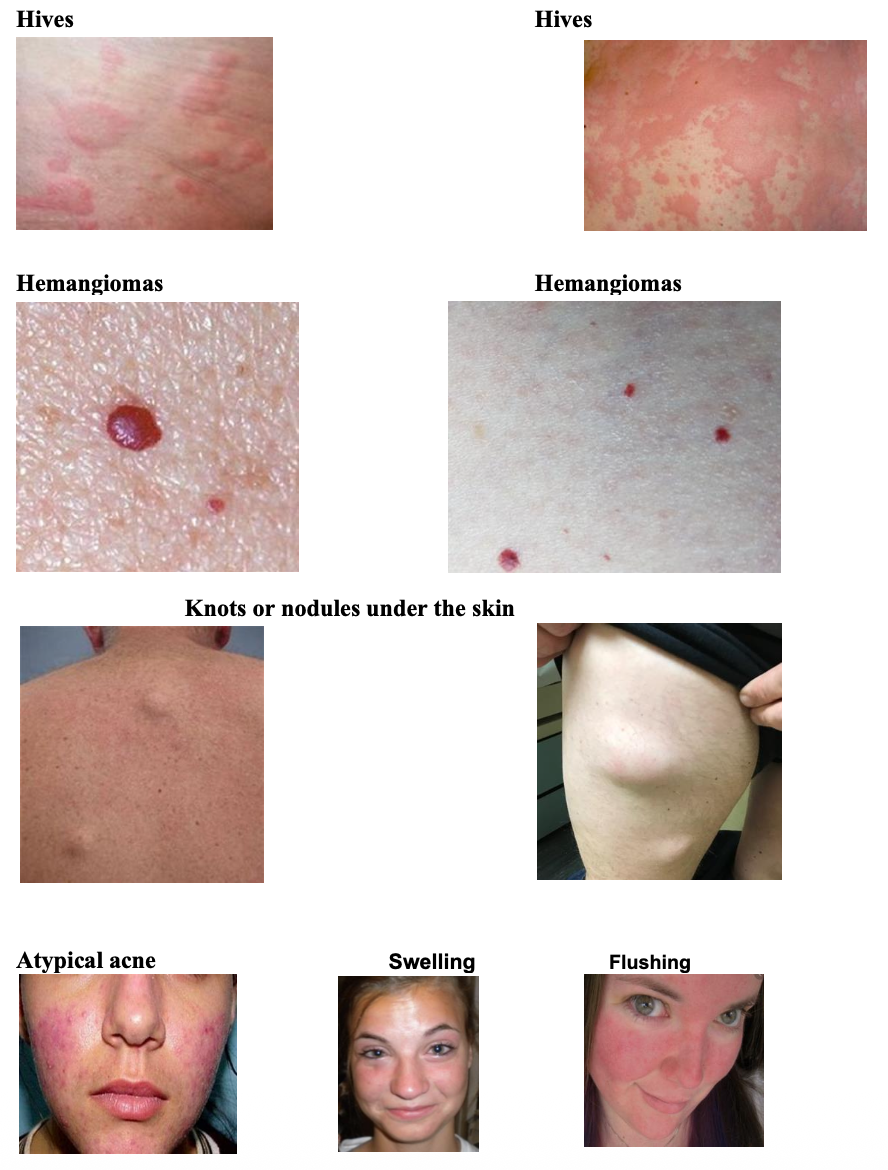
Mast Cell Activation Questionnaire Please enable JavaScript in your browser to complete this form.Name *Birth date *Date of completion *If the statement applies to you, select the intensity level from the dropdown next to it. The number should reflect how it was when it was last present. Use the range of 0 (not present) to 10 (unbearable) to reflect the level of your discomfort. INITIAL QUESTIONS Do you get colds regularly which then turn into bacterial infections such as bronchitis or sinus infections? *YesNoHas the course of your illness been episodic (and/or with attacks)? *YesNoHave the symptom-free periods become shorter and shorter? *YesNoIf the statement applies to you, enter the intensity level on the line next to the box. The number should be graded when it was present the last time it occurred. If the statement does not apply, do not check the box or enter a number. Use the range of 1 (very mild) to 10 (unbearable) to reflect the level of your ✓ discomfort. Example: 6 GENERAL HEALTH Significant physical weakness or fatigue doing everyday activities *--- Select Choice ---0 — Not present12345678910 — UnbearableExtreme fatigue attacks, hard to keep eyes open *--- Select Choice ---0 — Not present12345678910 — UnbearableAt times I lose weight despite maintaining my normal diet *--- Select Choice ---0 — Not present12345678910 — Unbearable EYES, EARS, NOSE, MOUTH Ears have ringing or odd sounds *--- Select Choice ---0 — Not present12345678910 — UnbearableEyes are dry, itchy, red, burning, or feel gritty *--- Select Choice ---0 — Not present12345678910 — UnbearableRunny or stuffy nose *--- Select Choice ---0 — Not present12345678910 — UnbearableInflammation or ulcers of the mouth *--- Select Choice ---0 — Not present12345678910 — Unbearable CHEST AND HEART Burning and/or pressure pain in the chest (Normal electrocardiogram or stress test; or not severe enough to go to ER) *--- Select Choice ---0 — Not present12345678910 — UnbearableRapid heart rate (rapid palpitations) *--- Select Choice ---0 — Not present12345678910 — UnbearableRedness or flushing of the skin, especially face or upper body *--- Select Choice ---0 — Not present12345678910 — UnbearableHot flashes (usually with dry skin lasting 2 to 5 minutes, rarely 10 minutes and often occur with nausea or other symptoms (these are not menopausal hot flashes with wet sweats) *--- Select Choice ---0 — Not present12345678910 — UnbearableSudden dizziness/lightheadedness with fainting or near faint *--- Select Choice ---0 — Not present12345678910 — UnbearableField #38 (copy) LUNGS Irritable dry cough or need to cough *--- Select Choice ---0 — Not present12345678910 — UnbearableFeeling of shortness of breath or difficulty taking a full breath *--- Select Choice ---0 — Not present12345678910 — Unbearable urgent altered Rapid Asthma-like complaints (wheezing) *--- Select Choice ---0 — Not present12345678910 — UnbearableField #38 (copy) (copy) ABDOMEN Attacks of visible bloating or distension within minutes *--- Select Choice ---0 — Not present12345678910 — UnbearablePain in the abdomen *--- Select Choice ---0 — Not present12345678910 — UnbearablePain is burning *--- Select Choice ---0 — Not present12345678910 — UnbearablePain is crampy or spastic *--- Select Choice ---0 — Not present12345678910 — UnbearablePain is associated with diarrhea (watery or loose stool) *--- Select Choice ---0 — Not present12345678910 — UnbearableNausea (with or without vomiting) *--- Select Choice ---0 — Not present12345678910 — UnbearableDo antihistamines help reduce nausea (examples: Allegra, cetirizine, Claritin, diphenhydramine, Xyzal, Zyrtec, etc.)? (this does not include nausea relief from Zofran or Ondansetron) *YesNoField #38 (copy) (copy) (copy) URINE/PELVIS Bladder and/or pelvic pain (this applies to women and men) and is often associated with painful, frequent and/or urgent urination 3 and may be associated with pain during sex. (during these times bacterial cultures and urine analysis are normal) *--- Select Choice ---0 — Not present12345678910 — UnbearableField #38 (copy) (copy) (copy) (copy) NEUROLOGIC and MUSCULOSKELETAL Migraine-like headaches (throbbing on one side only or have been diagnosed as a migraine – (these are NOT tension headaches) *--- Select Choice ---0 — Not present12345678910 — UnbearableBrain fog – word finding problems and/or concentration difficulties with or without associated insomnia episodes *--- Select Choice ---0 — Not present12345678910 — UnbearableNeuropathy: leg or arm pain and/or altered feelings including numbness, tingling, burning, sharp pain, and pins and needles.(this does not respond to over-the-counter pain medicine) *--- Select Choice ---0 — Not present12345678910 — UnbearableChronic muscle and/or joint pain and tenderness *--- Select Choice ---0 — Not present12345678910 — Unbearable(see the Photographic Examples at end) (copy) SKIN Hives (red raised itchy spots) *--- Select Choice ---0 — Not present12345678910 — UnbearableHemangiomas (raised or flat bright red spots) *--- Select Choice ---0 — Not present12345678910 — UnbearableDuring attacks there are itchy skin lesions that look like acne in the corners of the nasal-lip area, as well as, the chin and forehead *--- Select Choice ---0 — Not present12345678910 — UnbearableKnots or nodules under the skin *--- Select Choice ---0 — Not present12345678910 — UnbearablePainless, non-itchy swelling (especially lips, cheeks, eyelids) *--- Select Choice ---0 — Not present12345678910 — UnbearableItching in area around the anus during attacks *--- Select Choice ---0 — Not present12345678910 — UnbearableSudden, significant hair loss *--- Select Choice ---0 — Not present12345678910 — Unbearable HEMATOLOGIC Bruising after minor injuries *--- Select Choice ---0 — Not present12345678910 — UnbearableUnusual nose bleeds *--- Select Choice ---0 — Not present12345678910 — UnbearableWomen only: significant menstrual bleeding *--- Select Choice ---0 — Not present12345678910 — UnbearableAre your symptoms worsened by:High histamine foods (alcohol, cheese, chocolate, tuna, cured fish/meat, leftover meat, raisins, tomatoes)Sleep deprivation (awake more than 24 hours)Hunger or fastingField #62 (copy) BONE Bone pain that usually occurs in more than one bone *--- Select Choice ---0 — Not present12345678910 — UnbearableBone density test showed osteoporosis or osteopenia without a known cause *--- Select Choice ---0 — Not present12345678910 — UnbearableWhole-body nuclear scintigraphy showed areas of increased bone metabolism without a known cause *--- Select Choice ---0 — Not present12345678910 — UnbearableOverall health (0-100) *--- Select Choice ---0 — worst imaginable health5101520253035404550556065707580859095100 — best imaginable healthDo you have any symptoms as described below?an urge to move the legs usually in response to discomforting sensations in your legs and/or armsworsening of symptoms later in the evening or at nightworsening of the symptoms while at rest, i.e. lying or sitting; andat least partial and temporary relief by activityRLS is not jerking while sleeping, nervous foot tapping, or the need to move legs owing to back pain, arthritic pain, or sciatica.. Based on the above, Do you think you have restless legs syndrome? *YesNoSubmit SKIN PHOTOGRAPH EXAMPLE